Incidental Endometrioma: When Your Scan Finds Something You Weren’t Looking For
Have you been told you might have an incidental endometrioma and wondered how a scan for something else could leave you with so many questions? A few words in a report can turn an ordinary day into a long wait for an explanation. If you feel unsettled despite having little or no pelvic pain, you have every right to ask what the finding means for you.
An incidental endometrioma is an ovarian cyst linked to endometriosis, found on imaging done for another reason. A scan may suggest the diagnosis; your clinician can explain how certain it is and whether you need specialist review or follow-up. The finding alone does not mean you must have surgery.
My wife’s experience led me to spend years studying endometriosis as her husband, a blogger and researcher; I’m not a clinician, and I’ve listed the NICE, NHS and RCOG guidance I used at the end.
An unexpected report still belongs in the wider picture of how endometriosis is diagnosed, where your symptoms, imaging and priorities can each change the next step.
The word “incidental” tells you why nobody was looking for this finding when the scan was ordered. It doesn’t tell you how certain the finding is or whether it explains any symptom you already have.
Even an imaging appearance that strongly suggests an endometrioma doesn’t give you a complete map of endometriosis elsewhere. A useful conversation starts with the question the scan actually answered and identifies what still needs investigating.
My wife has lived with deep endometriosis, and learning how much information can sit behind a few words has made me appreciate how hard it is to wait for a proper explanation. Her experience cannot decide what your scan means, and I would never ask you to use her course as a forecast for yours.
You may leave the next appointment with an answer, or you may leave with a better question and a date to ask it again. Both are more useful than being left alone with a line in a report.
If a few words on a scan have brought up old worries about being heard, my free eBook is there for the emotional side of that wait. You can come back to it while your clinical team works through what the finding means.
You Did NOTHING To Deserve This!
Endometriosis Validation for Women with Endo

What an Incidental Endometrioma Can Tell You
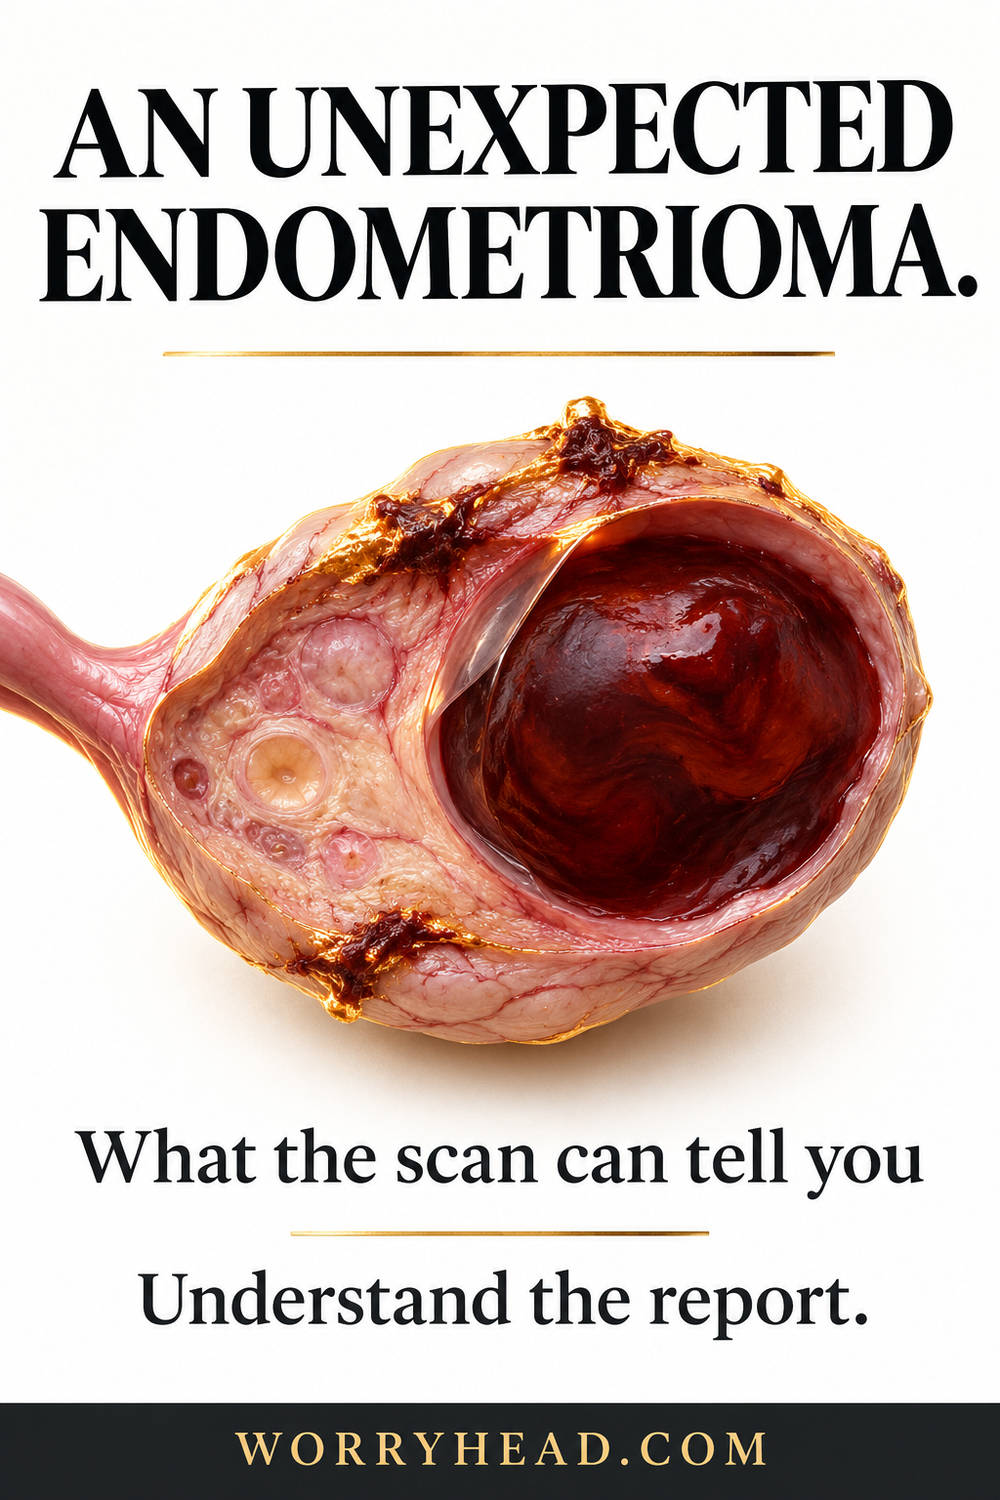
An endometrioma forms in an ovary and can contain old blood. Other ovarian cysts can also contain blood, so a clinician looks at the pattern on the images and the circumstances of the scan rather than giving one feature the final say. The report might name an endometrioma as its leading possibility or describe a finding that needs a closer look.
If your scan looked at the abdomen broadly, the ovary may have appeared near the edge of what the radiologist needed to assess. A more targeted pelvic scan can answer different questions. That does not mean the first scan was a mistake or that every reader needs another test.
A clinician looks at more than size: they may consider what the cyst looks like internally, whether an earlier scan shows the same finding and whether you are before or after menopause. Numbers in millimetres can feel precise enough to settle everything, but a measurement is only one part of the decision. The number is helpful because it describes what was seen, not because it predicts your future by itself.
When the report is available before the conversation, you might find yourself comparing its wording with someone else’s result online. Even if you find the same word, you won’t know whether the two scans were taken for the same reason or whether the radiologists were equally confident. A better starting point is to pick one phrase you need your own clinician to translate.
An incidental endometrioma can prompt a clinician to ask about symptoms you hadn’t connected to your cycle. Tell them if you’ve noticed painful periods, pain with sex, or recurring bowel or bladder symptoms. If these don’t apply, you don’t need to hunt for symptoms to justify having your result looked at.
You can also ask whether the finding has anything to do with the problem that led to the original scan. That problem may still deserve its own explanation even if the cyst is real. Fixing your attention on the newest finding can leave the original question unanswered.
I started writing because trying to support my wife meant learning to ask better questions, especially when I didn’t have the expertise to answer them myself. If I could sit beside you now, these are the things I’d help you get onto one manageable page.
- Read the Exact Wording
- Find the Scan’s Original Question
- Ask How Confident It Is
- Bring Earlier Imaging Reports
- Describe What You Actually Feel
- Agree Who Owns Follow-Up
- Name Your Personal Priorities
- Ask What Would Change Plans
Read the Exact Wording

Start with the report’s summary, sometimes labelled the impression or conclusion. Save the scan date as well as the sentence that names the finding. A description such as “likely” or “suggestive of” expresses the reader’s level of confidence; it does not mean every other possibility has already been ruled out.
If you can, print the summary or copy it into a note so you can point to it without having to remember its wording under pressure. You might have received only a verbal message; in that case, ask which clinician can share the written result and talk it over with you.
I know how easily unfamiliar vocabulary can make a conversation feel as though it’s happening around you. Your useful detail for this step is the exact wording, not a theory about what it means. Leave room beside it to write the explanation you get in plain English.
Find the Scan’s Original Question
Write down why this scan was arranged before you add any details about the cyst. You might have been investigated for bladder symptoms, abdominal pain or something entirely unrelated, and that context matters when the report is read. Ask what the scan did or did not show about that original problem.
If several issues were being investigated, keep each question separate on your note. The clinician who requested the scan can explain which problem their team will continue to follow and whether the ovarian finding needs a different service. It can help to ask who should bring those threads together if you get two separate letters.
I learned through my wife’s experience that one diagnosis doesn’t make every symptom suddenly easy to explain. Asking what remains unanswered is a reasonable way to protect the care you originally needed.
Ask How Confident It Is
A radiologist describes patterns, then explains which possibilities fit best. Your clinician can say whether the image looks fairly typical for an endometrioma or whether another kind of cyst remains a realistic possibility. You don’t need to learn how to identify any of those patterns on a screen by yourself.
Sometimes there’s a clear reason to ask for a more focused assessment, such as imaging that wasn’t designed to look closely at the ovaries. Sometimes the available images give the team enough information to decide where to refer you. Ask what the next step could clarify and whether it would change the plan.
If the answer is that some uncertainty will remain for a while, ask the clinician to explain what makes waiting appropriate in your situation. That gives you a reason behind the plan and a way to understand what new information might change it.
Bring Earlier Imaging Reports
An older report can be useful even if it was written for a different reason. Give your clinician the date, the hospital or clinic and, if you have it, the part of the report describing the ovaries. If the older images aren’t in the same system, ask whether the team can obtain them for comparison.
Not seeing a cyst mentioned previously doesn’t necessarily tell you when it appeared. An earlier test may have looked at different structures or been done with a technique that gave a different view. Even when the same area was assessed, ask the clinician how comparable the two sets of measurements are.
You don’t have to reconstruct your entire medical history in one evening. If all you can find is the month and name of the hospital, that still gives the team a starting point. Let them tell you whether they need more.
Describe What You Actually Feel

Come with a short account of what has been happening, if anything. A symptom list helps most when it says how often something happens, how it affects your day and whether it has changed. If you have pain, one example such as missing work can be more useful than trying to squeeze a year into a single pain score.
If you feel well, say that plainly. You don’t owe anyone a dramatic story for the report to deserve an explanation. If you’ve had symptoms for years but found ways of working around them, describe the workarounds too; what you’ve learnt to manage may still affect your life.
Watching my wife live with endometriosis taught me how much can be invisible when someone gets on with a task. In your appointment, the adjustments you make to get through it can be worth mentioning alongside the symptom itself.
Agree Who Owns Follow-Up
Before a call or appointment ends, ask who is responsible for telling you the result and arranging anything that follows. Write down the name of the service even if you do not have a person’s name. Ask which route to use if you hear nothing by the date they give you.
There can be a gap between a recommendation in a report and a referral being made. You can ask whether a referral has already been sent, whether it is awaiting review, and what you should expect to receive. If the plan includes another scan, check whether you’ll receive a separate booking message.
You shouldn’t have to manage the whole system yourself. The aim is to know where to go if the plan stalls, without having to retell your story to everyone. One written sentence about the next action can save a great deal of guesswork later.
Name Your Personal Priorities

Tell the clinician if your worries are mainly about pain, the possibility of needing treatment, or how a decision might affect your ability to have children. Those concerns can matter even when you have few symptoms. If fertility matters to you, say whether it is a present concern, a possible future one or something you would rather not discuss today.
What matters to you may differ from what seems obvious to someone else in the room. If you want to understand the impact on work or caring responsibilities, ask what attending follow-up or recovering from a proposed procedure might involve. When details are uncertain, ask what can reasonably be planned around them.
I think support begins with listening to what you’re worried about instead of choosing the worry on your behalf. If you take a partner along, give them a job you want done, such as writing down your questions.
Ask What Would Change Plans
An agreed period of observation should come with an explanation. Ask whether a change in symptoms, a particular change on repeat imaging or a clearer diagnosis would make the team recommend something different. That is more useful than leaving with the impression that every change automatically means surgery.
Also ask which changes should prompt contact sooner and which service to contact. There may be one answer for routine questions and another for sudden symptoms. If you are already waiting for an appointment, check what to do if the symptoms that brought you to care persist or start getting worse.
Write the instructions in your own words and read them back if that helps. You can put them alongside the next contact date, so the plan is there when you need it rather than being another thing you have to keep in your head.
How the Incidental Endometrioma Plan Is Chosen
A suspected endometrioma is different from a straightforward report of a simple ovarian cyst, so advice aimed at simple cysts may not apply to you. NICE recommends referral to a specialist endometriosis service when an endometrioma is suspected or confirmed. Referral gives the team a chance to interpret the finding and discuss what you need.
A specialist may want to look at the existing images before deciding whether another scan would help. Depending on the question, that might involve a targeted ultrasound or a different test, but neither should be assumed from the word “incidental” alone. Ask what the proposed test would add and when someone can explain its result.
If an internal ultrasound is suggested, you can ask why it’s recommended and talk about whether it’s suitable for you. Tell the team if an internal examination is painful or difficult, and ask what alternatives might be possible and what their limits are. You’re entitled to the information you need before deciding what you’re comfortable with.
After menopause, an ovarian finding can be assessed differently, so tell the team if that applies. The same is true if you could be pregnant or if you’re in fertility care. Your circumstances can change the questions the team needs to answer, even if the wording of the imaging report stays the same.
If it helps to take someone along, decide what you want them to hear or do before you arrive. My wife’s experience has shown me the difference between being available and taking over; a second person can write down the options and still leave the choices in your hands. If you prefer to speak without them for part of the appointment, that is equally reasonable.
Living With an Incidental Endometrioma While You Wait

Waiting is harder when you do not know what someone is waiting to learn. Ask whether the team wants a clearer diagnosis, a comparison over time or a conversation about a decision you might face. Those are three different reasons to wait, and knowing which applies can tell you what to expect next.
If surgery is suggested, ask why it’s being discussed now, what other choices are reasonable and what the trade-offs are for you. If you hope to have children, ask about possible effects on the ovary and whether fertility advice would help before you decide. You can also ask whether there’s time to talk through the decision at a separate appointment.
If you haven’t been offered treatment, it’s fair to ask whether that means the team recommends monitoring or whether the next decision depends on a specialist opinion. Those situations can sound the same in a hurried phone call but have different follow-up arrangements. Knowing what is already decided can make it easier to live with the part that isn’t.
I see why someone might cancel plans after a result like this even when they physically feel as they did the day before. You can tell one person why you’re worried without opening up a conversation with everyone you know. And you can choose to go ahead with something you enjoy while a result is being reviewed, following any specific advice the clinical team gave you.
When to Seek Medical Help?
The NHS advises seeking urgent help for sudden, severe pelvic pain or if you have abdominal pain together with nausea or vomiting. In the UK, contact NHS 111 or arrange urgent medical assessment. If the pain is severe and worsening, or you feel faint or collapse, seek emergency help rather than waiting to see whether it’s connected to the cyst.
If pregnancy might be possible, tell the service that when you describe any new pain or bleeding. A known ovarian finding should not be used to explain a new symptom without an assessment, because other conditions may cause similar symptoms. Give the service the timeline and tell them what has changed.
For symptoms that are less urgent but recurring, or that affect your day-to-day life, arrange a routine clinical review and mention both the scan result and the original reason you had the scan. If you don’t know who is responsible for explaining the result, start with the GP or clinic that requested it. Keep the scan date handy so the team can find the correct report.
Questions to Ask Your Doctor
Choose the questions that matter most to you and put your first one near the top of your note. I’d start by asking for an explanation of the result in a sentence I could repeat at home. When the conversation turns to appointments, ask for the next action as clearly as you would ask for the name of a medicine.
- How strongly does the imaging suggest an endometrioma, and what else could fit?
- Does this result explain the reason for my scan, or is that question still open?
- Can you compare the images with an earlier scan, and would that change your advice?
- Is a referral to a specialist endometriosis service appropriate, and who will arrange it?
- What would another scan clarify, and how will I get the result?
- If treatment is being discussed, what are the benefits, risks and alternatives for me?
- Who should I call if my symptoms change or I do not hear by the agreed date?
If you are short of time at the end, ask for a written summary or where you can see the plan in your records. It’s reasonable to say you need to check your understanding before you leave. You can ask the clinician whether your interpretation is right rather than trying to capture every word they said.
Final Word on Incidental Endometrioma
A result that arrives unexpectedly can divide your day in two. Before it, you were dealing with whatever brought you to the scan; afterwards, a second question has arrived with no obvious place to put it. If you feel like you should already know what to do, it may help to start with what nobody has told you yet: why the person who read your images used those particular words, and whether your clinical team agrees with that interpretation.
An incidental endometrioma may turn out to be something your team keeps an eye on, or it may prompt more assessment. Neither possibility tells you in advance which care will be right for you. I would want you to have enough detail to understand why your team recommends one thing rather than another. If you don’t get that in the first conversation, it’s reasonable to ask who can give you a better explanation.
Part of what I learnt from living beside endometriosis is that practical help is often very ordinary. Somebody remembers the name of the clinic. Somebody makes lunch while you sit on the phone. A partner can help you get your thoughts into a few lines, and then let you speak when the clinician asks what you want. You may find that kind of company useful, or you may want a quiet hour on your own.
I also want you to be able to talk about the original reason for the scan. An unexpected finding can attract the whole room’s attention, and you may still be waiting to know why you have the symptoms that brought you there. Bring that question back even if the first appointment spends most of its time on the new result. You deserve a plan for both questions when they are separate.
There may be a point when a decision involves more than knowing what the image shows. Consider what you most want to protect: your comfort during an examination, time away from work, a fertility decision or simply enough information to say yes or no. Whatever your priority, it helps the clinician understand what a good outcome would look like from your side of the desk. You can name more than one.
Some things can wait for the agreed review, and a sudden change in how you feel may need attention sooner. Knowing which service to call can let you put the report away for an afternoon. If you feel drawn to searching the same words again, it might be kinder to use that time to write down the question the search keeps leaving unanswered. Then make sure you know who you will ask it.
If you only have energy for one thing today, find out who will explain the result and when you should expect to hear. A named service and a realistic date won’t answer every question, but they give your worry somewhere to go. Your report is a piece of information about you, and you’re entitled to have it explained.
You can take this one conversation at a time. Write down the words that puzzled you, keep the contact details close, and let someone help with the practical bits if you want them to. There is no test of how calmly you should handle an unexpected result. You deserve answers you can understand and a plan you can come back to.
If you’d like to share what helped you during the wait, you’re welcome to leave a comment. My free 130+ page eBook below offers company for the days when an endometriosis question is taking up more space than you wanted it to.

About Me
Hi, I’m Lucjan! The reason why I decided to create this blog was my beautiful wife, who experienced a lot of pain in life, but also the lack of information about endometriosis and fibromyalgia for men…
READ MORE
Grab a FREE eBook!
“You Did NOTHING To Deserve This!”
Finally hear the words nobody ever said to you, that your pain is real, your tears make sense, and you did nothing to deserve endometriosis, the dismissal, or the way it has rewritten your life.
Related Questions You May Be Asking About Incidental Endometrioma
Can an endometrioma be found when I have no pelvic pain?
Yes. An imaging finding can be noticed while the clinician is investigating something else, including when you don’t have pelvic pain. Tell the clinician honestly how you’ve been feeling. They can put the imaging appearance alongside your history and explain whether it warrants specialist review or further assessment.
Does the phrase “consistent with” mean I have a confirmed diagnosis?
It usually means the appearance fits a particular explanation, but the level of certainty depends on the rest of the report and the quality of the images. Ask the clinician what other possibilities are being considered and what, if anything, would distinguish them. You don’t need to interpret the phrase on its own.
Can I bring the report to a fertility appointment?
Yes. You can share it with the fertility team and ask them to coordinate with the clinician reviewing the finding. If someone suggests an operation, ask how it could affect the ovary and whether it should be discussed with your fertility team before a decision. What’s right depends on your individual priorities and circumstances.
Should I wait for a referral if the pain suddenly gets worse?
Don’t wait for a routine referral if you develop sudden, severe pelvic pain or abdominal pain with nausea or vomiting. The NHS advises urgent assessment for these symptoms. If you are very unwell or feel faint, seek emergency help. An urgent assessment can consider the cyst and other possible causes.
What if the finding is on the other side from my usual pain?
Tell the clinician where you feel the pain and when it happens, even if it doesn’t seem to match the report. The location of a cyst doesn’t establish the cause of every symptom. Ask whether the reason for your original scan needs to be assessed separately and whether there’s any other relevant information on the images.
Incidental Endometrioma References
- https://www.nice.org.uk/guidance/ng73/chapter/Recommendations
- https://www.nhs.uk/conditions/ovarian-cyst/
- https://www.nhs.uk/symptoms/pelvic-pain/
- https://www.rcog.org.uk/for-the-public/browse-our-patient-information/ovarian-cysts-before-the-menopause/
- https://www.rcog.org.uk/gtg34/
