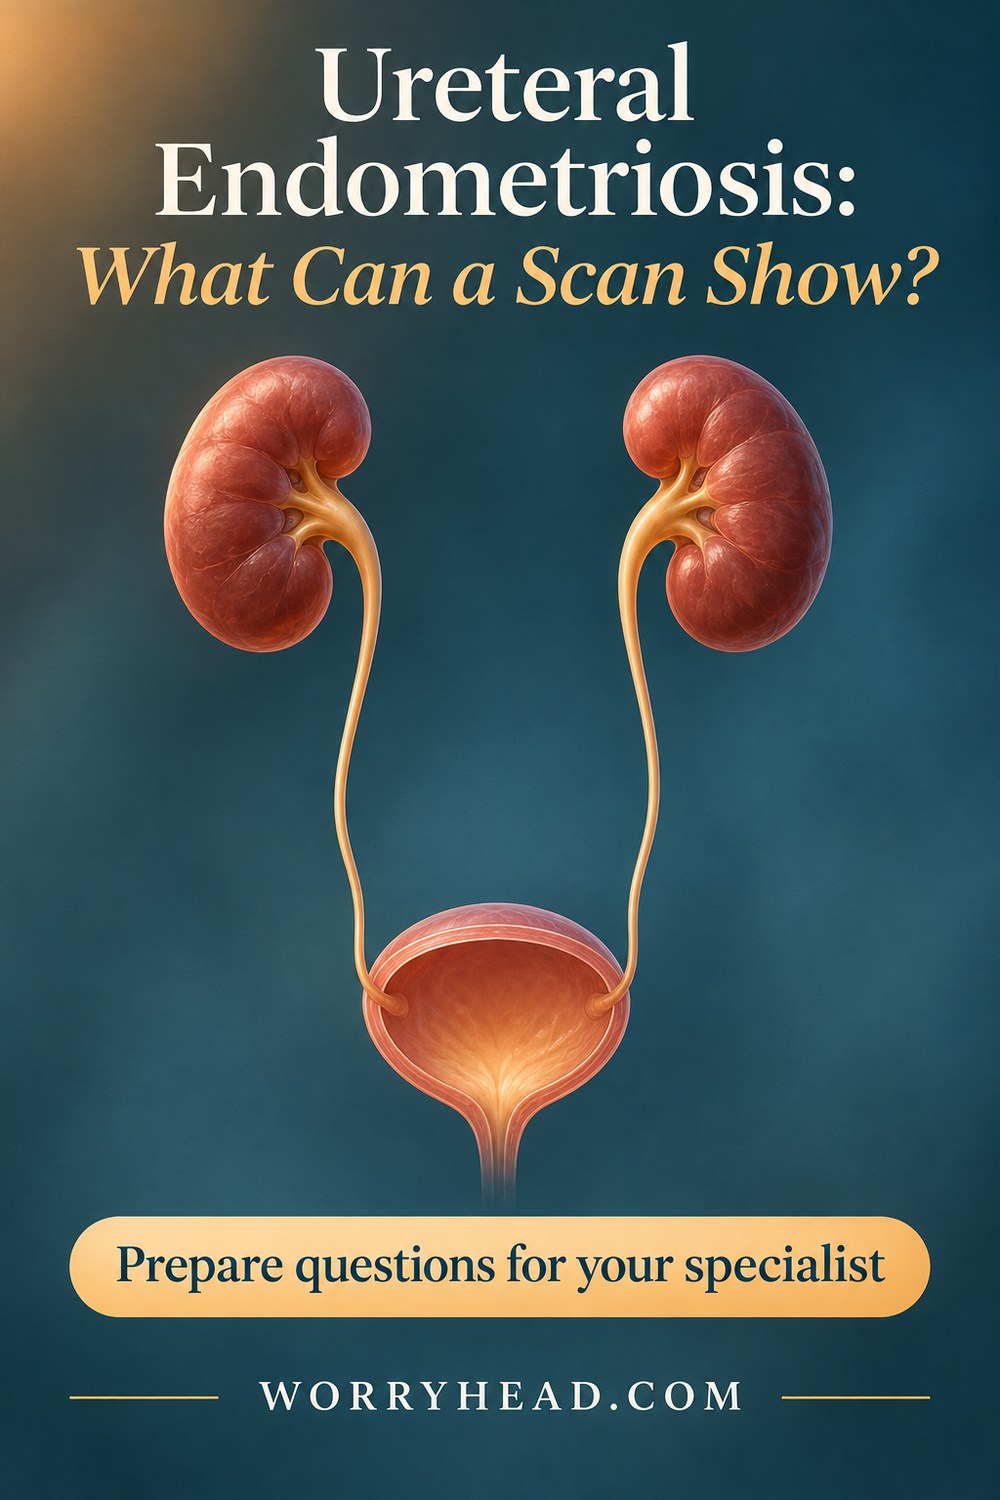
Ureteral Endometriosis: What a Scan Can Tell You About Kidney Drainage
Has a scan or specialist letter mentioned ureteral endometriosis and left you wondering why your kidney is part of the conversation? It can be unsettling to read a new term when you already have more than enough symptoms to think about. You deserve to know what the team has found, what still needs checking and who will explain the plan.
Ureteral endometriosis affects a tube that carries urine from a kidney to the bladder. It can narrow the tube and affect kidney drainage, sometimes with few symptoms. Ask your specialist which side is involved, whether the kidney is swollen, what needs checking and how soon you should be seen next.
I’m a husband, blogger and researcher who has spent years learning through my wife’s experience; I’m not a clinician, and I list the NICE, NHS and specialist society guidance I used at the end.
If you want to place this finding in context, my guide to the different types of endometriosis explains where disease can occur. Here I’ll focus on what involvement of a ureter might mean for the checks your team considers next.
The ureter carries urine down from a kidney, while the urethra carries urine out from the bladder. Knowing which tube the report refers to makes it easier to ask what the clinicians are concerned about.
A scan might describe tissue near a ureter, suggest that the tube is narrowed or show swelling higher up towards the kidney. Those findings answer different questions, and the team may need more information before saying what is causing a problem.
My wife’s deep endometriosis affected several parts of her pelvis, including her bladder. Supporting her taught me how valuable it is to ask what a finding means for the organ involved rather than assume that I understand a report because I recognise the name of the condition.
If you have a report in front of you, look for which side it names and what the team said about drainage. Leave the interpretation to your specialist and use the wording to frame your questions.
If the scan has left you with more on your mind than you expected, my free eBook is there when you have time for it. I wrote it to offer some company on the days when there is a lot to take in.
You Did NOTHING To Deserve This!
Endometriosis Validation for Women with Endo

- What Ureteral Endometriosis Can Mean for Your Kidney
- How Specialists Investigate Possible Ureteral Endometriosis
- After a Ureteral Endometriosis Review, Keep the Next Step Clear
- When to Seek Medical Help?
- Questions to Ask Your Doctor
- Final Word on Ureteral Endometriosis
- You Did NOTHING To Deserve This!
- FREE eBook
What Ureteral Endometriosis Can Mean for Your Kidney
There are two ureters, one leading from each kidney to the bladder. Endometriosis can affect tissue around a ureter, and sometimes the wall of the tube itself. Tissue around the tube can narrow it from the outside, so a report need not describe disease inside the tube for drainage to need attention.
A scan that shows tissue close to the ureter is not the same as a scan that demonstrates obstruction. The specialist needs to interpret where the tissue lies and whether it is affecting drainage. If the findings are uncertain, ask which part of that question the next investigation is intended to answer.
When urine does not drain properly, the collecting system in a kidney can widen. This is called hydronephrosis. It has several possible causes, and the term alone does not establish that endometriosis is responsible.
Ureteral endometriosis can be present with few symptoms. Feeling little pain does not tell you whether the kidney drains normally. That is one reason to follow the team’s advice about checks rather than wait to feel worse before taking a result seriously.
NICE recommends referral to a specialist endometriosis service for suspected or confirmed deep endometriosis, including disease involving a ureter. These services should have access to urology expertise. If a ureter is involved, you can ask whether both gynaecology and urology need to review the findings.
A team may use different tests to assess the location of suspected disease, how urine drains and how well the kidney is working. Which investigations you need depends on the findings and the question being considered. Ask what each test is intended to clarify and who will put the results together.
I have learned beside my wife to start with the part of an explanation that changes what we do next. That is the purpose of the list below.
- Find Which Side Is Involved
- Separate Location From Blockage
- Ask What Swelling Means
- Clarify Which Scan Checks What
- Ask About Kidney Function
- Find Out Who Is Involved
- Understand the Timing of Care
- Write Down the Follow-Up Plan
Find Which Side Is Involved

Find out whether the report describes the left ureter, the right ureter or both. The wording may refer to the area where the ureter runs rather than the ureter itself. Ask the specialist to point out which part of the anatomy the report is describing and what they think is important about it.
You can also ask whether the report comments on the kidney on the same side. If it does not, the scan may have been looking at a narrower part of the body or answering a different question. Check with your team whether the kidney and its drainage need a separate assessment.
Keep the side and the date together when you make your notes. If you have more than one scan, check that you are looking at the result the clinician is discussing. That can make a short conversation easier to follow, particularly if several findings use similar language.
Separate Location From Blockage
Tissue close to the tube and evidence of a blockage are different findings. Ask whether the team is describing what lies nearby, how wide the tube looks or whether urine is having difficulty draining. One scan may offer useful clues without answering all three questions.
If a report mentions suspected deep disease next to a ureter, ask what the finding changes about your next steps. This might depend on whether the ureter is still draining and whether the team needs more detail for planning. You can ask how confident they are and what would clarify the part that remains uncertain.
It helps to write down the clinician’s answer instead of trying to infer it from a phrase such as close to or abutting. I know how easily I can make a report sound more definite in my head than it was on the page. You can ask to hear that distinction in ordinary language.
Ask What Swelling Means

Hydronephrosis means the collecting system in the kidney has become widened. A scan may describe how pronounced it looks, but the word does not tell you what caused it or how the kidney is working. Ask whether the team thinks drainage is obstructed and what further checks could clarify the cause.
If you have a new result and do not know whether a clinician has seen it, contact the team that arranged the scan. Ask what the finding means for the timing of your next assessment and whether another specialist needs to be involved. Do not wait for pain to develop to ask about an unexplained finding.
Other conditions can affect urine drainage, including kidney stones. A history of endometriosis does not settle the cause of the swelling. The useful question is what the clinician is doing to determine why the kidney looks that way and how quickly it needs attention.
Clarify Which Scan Checks What
A pelvic scan and an assessment of the kidneys can have different purposes. Specialist pelvic imaging may be used to assess the location and extent of deep disease. An ultrasound that looks at the kidneys can help the team check for swelling associated with drainage problems.
Ask what was included in the scan you already had before assuming it has answered the question about your kidneys. If you are sent for a different scan, ask which information the team wants from it. You may be able to avoid carrying the whole story yourself by checking whether the service can see the previous report and images.
The result of any test should be explained in the context of the clinical question. If a report looks less clear than you expected, ask which question it did answer. That can help you see why a further check is planned or why the specialist is confident that one is not needed at this stage.
Ask About Kidney Function

How well a kidney works and whether urine drains from it are related questions. Clinicians may use blood tests, imaging or other tests depending on the situation. Ask whether a particular result is about overall kidney function or gives information about the kidney on the side that concerns them.
If the team mentions checking one kidney separately, ask what they need to know before deciding on care. You do not need to recognise the name of every test to ask what it measures, who will explain it and what effect the result could have on the plan.
Do not try to decide that a normal result means there is no drainage issue without asking what the test was meant to assess. A specialist can explain how the results fit together. If the team is still waiting for information, ask how they will keep you informed and whether you need advice before the next appointment.
Find Out Who Is Involved
A gynaecology team may assess how suspected deep endometriosis affects the pelvis, while a urologist can advise on the kidneys and urinary tract. Depending on the case, the teams may review imaging together. Ask who is coordinating your care and whether another appointment or team review is being arranged.
The specialist best placed to answer one question may not be the person who gives you the next appointment. Try to find out which team will tell you about the results and how they will share information with the other clinicians. This makes it easier to know where to go if you receive two different letters.
I find that a job is easier to share once I know who is expected to do it. Write down the name of the service that will contact you and who you can call if the date passes without news. Ask for a practical description of the next step if you still feel unsure.
Understand the Timing of Care
If a ureter is thought to be obstructed or a kidney is swollen, ask the clinical team how quickly a review is needed. The answer can depend on the imaging, kidney function and how well you are. Pain alone is not a safe way to decide how soon the finding should be assessed.
Some people need further tests to establish whether there is a blockage or what is causing it. Others need treatment to protect drainage. Ask whether the team is making a decision now or waiting for a particular result, and what you should do if you are concerned before you hear.
If a planned appointment seems far away and the report mentions possible obstruction, get in touch with the team that arranged the investigation. Ask them to confirm the timing with someone who can review the findings. You should not have to guess whether a routine date is appropriate on the basis of the words in a letter.
Write Down the Follow-Up Plan
Try to finish the conversation knowing the next test or review, who is arranging it and what you should do if you have not heard by an agreed date. If you are given different contacts for symptoms, appointments and results, note which route to use for each.
A plan may also need to cover what happens once a result is available. Ask whether you will receive an appointment, a phone call or a letter and who will put the findings together. If another service needs the records, check whether you have to do anything to make that happen.
You can ask for written information you can look at later, particularly if you have had a lot to take in. Keep the summary short enough to use on a difficult day. Once the immediate plan is clear, you may have more space to think about other questions you want to raise.
How Specialists Investigate Possible Ureteral Endometriosis
A specialist may start by asking what previous scans or surgery showed and whether your records mention a possible problem around a ureter. Those details can help decide which area needs looking at. The team will also want to know about symptoms in case they suggest another problem that needs attention.
NICE recommends considering specialist transvaginal ultrasound or pelvic MRI to assess suspected deep endometriosis and its extent. This recommendation is about specialist examination and interpretation. A scan looking mainly at the pelvis does not automatically answer a separate question about how the kidneys are draining.
The joint surgical recommendations from ESGE, ESHRE and WES describe checking for hydronephrosis and assessing kidney function where ureteral involvement raises concerns. Individual assessments differ and not everybody is offered the same test. Ask the team what they are trying to establish before you read too much into a test name.
I have watched how hard it can be for my wife to explain one finding while trying to understand several others. If your report contains a long list, ask which item changes the next step now. That can help you put the questions in a useful order without having to ignore the other things that matter to you.
When the Report Leaves a Question
The person explaining your scan may say that it shows a possible finding but does not settle what caused it. Ask what the team thinks is most likely and whether any other possibilities need checking. It may be useful to compare the current result with a previous scan that looked at the same area.
If two reports use different language, you can ask whether they describe the same finding in a different way or whether the picture has changed. There might also be a difference in what each scan could see. Your specialist can tell you whether that difference affects what should happen next.
If the report has been discussed by a team, check what question they were looking at. A note may be about where disease sits rather than a full opinion on your kidney. You can ask who will explain the part of the report that still concerns you.
Ask What Is Being Protected
Treatment decisions may involve protecting kidney drainage as well as managing pain and other symptoms. If an obstruction is suspected, the priority may be to check how much urine flow is affected and how well the kidney is working. Ask the team to explain how those findings relate to the options they are recommending.
Some people are offered procedures to help drain a kidney or surgery to address the cause of the obstruction, depending on the facts. A suspected finding near a ureter does not automatically mean you need any particular operation. You can ask what your team expects each option to achieve and what could happen if care is delayed.
I would want to know who can answer the questions I think of after a difficult appointment. Ask whether you can speak to the relevant specialist again, especially if a decision involves weighing risks you have not discussed before. It helps to know when the team needs your answer.
After a Ureteral Endometriosis Review, Keep the Next Step Clear

You may hear a lot of information about the pelvis and only a small part about the kidney. Listen for the question that has consequences for what happens next. Ask the clinician to repeat the plan for drainage or monitoring if that is the part you are least sure about.
If a team is arranging a further test, find out whether you need to book it or wait for them to contact you. Ask when you should hear the result and which clinician will explain it. If someone mentions checking a kidney again later, ask what would make them bring that check forward.
Some decisions depend on findings that are still being gathered. You can ask about options provisionally without assuming the first one mentioned will be the final plan. If there is something you need to decide while you are waiting, ask how much time you have.
My wife’s experience has made me pay closer attention to what a plan asks of someone at home. That might be finding transport, arranging time off or simply having a number to call without searching through letters. You can ask to make those details part of the discussion so the next action is clear when you need it.
Arrange for Results to Reach You
Ask who will contact you after each test and what happens if they cannot reach you. Give the service a way to get hold of you that you can use. If someone else helps you keep track of dates, you decide whether you want them to see the letters or have access to your notes.
You can ask for confirmation that the relevant information has reached both teams if your care is shared. That can matter when gynaecology is waiting for urology advice or when the assessed area was outside a team’s usual remit. Find out who can help if one service has not received the records.
If you have a date in mind for following up, write it down. A patient portal, letter or phone message may be one part of the communication, but you still need to know who can address a question that was not answered by it.
Keep Symptoms and Findings Connected
If symptoms change, write down what happened and when, and seek the appropriate advice. You may be dealing with pain or urine symptoms for a reason other than endometriosis. Your clinician should have the opportunity to consider new information rather than assume everything belongs to the same diagnosis.
You can ask about ongoing symptom support while a decision about the kidney is being made. Those issues may be handled by different people. Knowing which team is responsible for each part of your care can help you get advice without having to repeat the whole story each time.
I have learned beside my wife that time and energy are things you can spend only once. If the plan feels like more than you can manage, tell the team which part is difficult to arrange. Ask for the most important action in writing so you can come back to it when you need to.
When to Seek Medical Help?
If a report newly mentions hydronephrosis or suspected obstruction and no one has discussed it with you, contact the clinician who arranged the scan promptly for advice. Ask who is reviewing it and how quickly you should be assessed. Do not assume it can wait until symptoms change.
The NHS advises urgent assessment for symptoms that may suggest hydronephrosis. These can include pain in the side or back, difficulty passing urine, blood in your urine or a high temperature or shivering. In the UK, contact an urgent GP service or NHS 111 for advice, and use emergency services if you are seriously unwell or have emergency symptoms.
For severe or worsening pelvic pain, or pelvic pain with faintness, heavy vaginal bleeding or difficulty breathing, call 999 or go to A&E in the UK. Follow any more specific advice your own team gave you about a known drainage problem. If you are elsewhere, use your local urgent care and emergency services.
Questions to Ask Your Doctor
Bring the report or make a note of its date if that is easier. Start with the question about whether the kidney is draining and how soon you need to be seen again.
- Which ureter does the report describe?
- Is there evidence that urine is not draining properly or that the kidney is swollen?
- Was the kidney seen on this test, or does it need a separate assessment?
- How will you check whether the kidney is working as expected?
- Does a urologist need to review the findings with the endometriosis team?
- Who will contact me and when should I follow up if I have not heard?
- Which changes should prompt urgent advice while I wait?
Ask whether there is a short version of the plan you can take away. If important information is still missing, write down which test or clinician will address it. That can help you keep the questions in order while you wait.
Final Word on Ureteral Endometriosis
Finding a new term in a report can make everything else you have been told harder to hear. You might already be trying to understand your pain or work out which treatment fits your life. Now there is a question about your kidney as well. Start by asking which side is involved and whether the team thinks there is a problem with urine drainage. You can ask how they know and what still needs checking.
Ureteral endometriosis matters because the tube that carries urine can narrow. How much pain you feel does not answer the question of how well that kidney drains. The clinical team can explain what your scan shows, whether there is swelling and what information will help them decide on the right next step. You can bring the report to the conversation without expecting yourself to interpret it.
I have watched my wife come away from appointments with more than one area of her body to think about. It takes a great deal of energy to work out which question belongs to whom. I find that there is real value in knowing the name of the person or team responsible for explaining the next result. That is something you can ask for even if the whole plan is still being put together.
A good follow-up leaves room to discuss the symptoms you live with and the risks the specialists are looking at. Those parts of the conversation may need different sorts of attention. Tell the team what is hardest to manage day to day, and find out what advice you can use if it gets worse. Ask where to turn if the problem becomes urgent before a scheduled review.
If another specialist is being asked to help, find out how you will hear what they advise. The person who requests a test and the person who explains it may not be the same. You can ask what will happen to the results and whether you will have a chance to speak about them rather than receive a report you have to decipher.
A diagnosis can make some things clearer while leaving questions about treatment. If a procedure is suggested, ask what it is intended to change and what the team is trying to protect. Ask what they would advise in your situation and when a decision is needed. You can get a clearer explanation without promising yourself that every part of the choice will feel easy.
For me, helping begins with recognising that the person who lives with the condition should not be left to connect all the pieces alone. If you need it, ask your team for a written plan. You can then give yourself time to think through the rest. A note showing exactly how to reach the right team can be more valuable than a longer explanation you cannot use at home. You can also ask whether your usual clinician will receive the same plan after your appointment, so they know what is happening.
Get clear on the next test, who is looking after it and how you will hear what it shows. If any part of that is missing, you can ask the team to go through it again. The questions about your kidney deserve timely answers, and you deserve enough support to take the next step when it comes. You can start with that one question.
If you want to share what helped you understand a scan result, you are welcome to leave a comment. My free 130+ page eBook is here if you need some company while you make sense of what you have heard.

About Me
Hi, I’m Lucjan! The reason why I decided to create this blog was my beautiful wife, who experienced a lot of pain in life, but also the lack of information about endometriosis and fibromyalgia for men…
READ MORE
Grab a FREE eBook!
“You Did NOTHING To Deserve This!”
Finally hear the words nobody ever said to you, that your pain is real, your tears make sense, and you did nothing to deserve endometriosis, the dismissal, or the way it has rewritten your life.
Related Questions You May Be Asking About Ureteral Endometriosis
Can it affect only one ureter?
Yes. A problem may affect one side or both sides. Ask which side your report refers to and whether the team has been able to assess the kidney on that side. If another test is planned, ask whether it will answer a question about the ureter, the kidney or both.
Does hydronephrosis mean I have ureteral endometriosis?
No. Hydronephrosis describes widening of the kidney’s collecting system and can have different causes. Ask what the clinician thinks is affecting drainage and whether they need additional information to confirm it. If you have endometriosis, it is still important to check other possible reasons for the finding.
Can I have a problem with drainage without strong pain?
Yes. Endometriosis affecting a ureter can cause few symptoms, so the amount of pain you feel is not enough to tell how well a kidney drains. Ask what checks your team recommends and when. Contact them if you have an unexplained result and nobody has told you what to do next.
Does a pelvic scan always check both kidneys?
A scan has a particular purpose, and the area it covers depends on why it was requested. Ask whether the team saw both kidneys and what they were able to conclude from the images. If it did not cover the kidneys, check whether another scan is necessary in your situation.
Will I need an operation?
That depends on what the team finds, including whether there is a blockage and how the kidney is working. Ask what the different options aim to achieve and how quickly you need to decide. If surgery is recommended, ask which specialists will be involved and how they will check the result afterwards.
Ureteral Endometriosis References
- https://www.nice.org.uk/guidance/ng73/chapter/Recommendations
- https://pmc.ncbi.nlm.nih.gov/articles/PMC7013143/
- https://www.nhs.uk/conditions/hydronephrosis/
- https://www.nhs.uk/symptoms/pelvic-pain/
